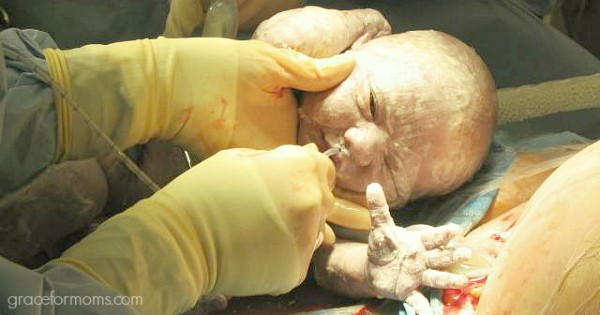
As I hold the scalpel over the patient’s abdomen, I notice my clenched hand is shaking ever so slightly. Taking a deep breath, I loosen my grip but can still feel the adrenaline in my veins. As I wait for anesthesia to insert the breathing tube so I can start the c-section, I reluctantly glance at the clock: 3:08 am. The baby’s heart rate has been low for 12 minutes. The only vital sign we have on a baby in labor is the heart rate, and right now the baby is telling me that he’s not getting enough oxygen. This is a true emergency. Anxiously, I look across the blue drape and see the CRNA is almost finished putting the patient to sleep. Once he confirms the breathing tube is in the right spot, he makes eye contact and barks a forceful “Go!”
The scalpel hits the skin immediately, splaying it open with one smooth swipe. Two more swipes through yellow globular fat and I hit the glistening white fascia layer. If this weren’t an emergency, I would stop to carefully cauterize the small bleeding blood vessels in the fat layer, but there is no time for that now. I nick the middle of the fascia, until I see the deep burgundy of the rectus muscles underneath. Quickly, I then slide my fingers under the fascia and with two forceful movements, I spread the fascia and muscles open with my fingers.
Thankfully, she’s not had a c-section before or I would have to stop and carefully cut the fascia and peal off the scar tissue wasting precious seconds. Next I push my finger through the final layer of the abdominal wall: the peritoneum. I glance at my assistant and say “pull”. We apply outward traction to the incision in unison and the open abdomen lays before me. The experienced scrub tech places a bladder retractor in my hand before I can even ask for it. Next I must quickly judge the best place to make the incision on the uterus. The lower uterus is swollen from the labor and the anatomy is distorted, making it difficult to identify the ridge that represents the edge of the bladder. The incision can’t be too low or the bladder could be damaged {the bladder is actually attached to the uterus}. If it’s too high the muscle is too thick, making it difficult to open and if I go too deep, I could cut the baby. I pick my spot and cut the uterus.
The final challenge is getting the baby out. As I open the uterus, instead of seeing a forehead or an ear, I see the baby’s shoulder. Sliding my hand into the uterus and guiding out the baby’s head is a fun simple step in a scheduled c-section, but when the patient has been pushing for hours the head can be stuck firmly, deep in the pelvis. That was the case here. The patient was pushing well, but the pelvis was too tight and the baby’s head was like a cork fitted firmly in a bottle, swollen into a giant squishy cone shape. The swelling made it difficult to wedge my hand between the head and the pubic bone. I tried to use a rocking motion, to wiggle my hand deeper into the pelvis, but the head wouldn’t budge.
“I need a hand from below,” I shout to the nurse. She then climbs awkwardly under the drape, between the patient’s legs. In the darkness she quickly inserts a hand through the vagina and into the birth canal. She pushes up on the head, dislodging it from the pelvis, so that I can get my hand around the top of the conehead. For a brief moment my fingers meet the nurses fingers. This is such a strange sensation, to touch through opposite ends of a open body. As I pull the head out of the pelvis, I can feel the malleable bones of the head squish and a “slurping pop” sound is heard as the baby is delivered. I quickly cut the cord and hand the limp blue baby to the NNP {neonatal nurse practitioner}. I say a prayer under my breath until I hear the baby respond to the oxygen and stimulation.
It took me 90 seconds to get that baby out. It felt like three hours.
Later I drove home through a thunderstorm. Luckily, I still had adrenaline coursing through my veins to keep me awake, but with the torrential downpour it was difficult to see the road. It occurred to me that doing a c-section is in some ways like driving a car. It’s mostly second nature, but in certain situations can be extremely challenging.
I’ve adapted this analogy to help explain to my patients the risks of different types of c-sections. Not to create fear, but to help them understand the risks of c-section can definitely vary depending on the circumstances.
A planned primary (first) c-section, when the patient is not in labor is the easiest, lowest risk type of c-section. This is like driving a car on a nice sunny day with no other cars around. You can see for miles and take your time to stop and take pictures. Sure there is always a risk of an accident, though it’s not very likely.
A scheduled repeat c-section can sometimes add challenge. Scar tissue from the first c-section can distort anatomy and make it difficult to get the bladder to peel off the uterus. This is like driving a car on a nice sunny day, but add in some traffic. The more c-sections you’ve had, the more traffic to dodge.
A c-section in labor is more challenging still. The tissue is swollen and distorted from labor. This is like driving at night in traffic through a construction zone.
A c-section on a VBAC (vaginal birth after c-section) in labor, creates another layer of difficulty due to the scar tissue. This is like driving at night, through a construction zone in the pouring rain, you can barely see the road.
An emergency c-section on a VBAC with a ruptured uterus is the worst case scenario. This is like driving through a construction zone at night, with pouring rain so hard you can barely see the road, while someone is throwing grenades at you.
If, in any of the cases, the patient is obese {like 35% of the population currently is} that ups the difficulty factor significantly, say like the power steering going out in your car. And if the baby’s heart rate has dropped, I must go fast. Then it’s like driving in any those challenging situations, but as fast as you possibly can.
It’s common when I talk to patients about the risks of labor, for them to pretty flippantly say something to the tune of “Well, if anything goes wrong, you can just do a c-section, right?” While that is technically true, a c-section is major surgery and always has risks, and with the risks being higher the more challenging the situation.
I hope this look inside the reality of a c-section gives you insight into what really goes on. As always, I encourage you to talk with your doctor about your options and potential risks so you are best prepared for the birth of your child, however he or she enters the world.
Did you have an emergency c-section? If so, do you think there was anything the doctor could have done to make it less scary?

This was a really interesting post, thanks! I’ve had a “#3” (exactly like you described in this post) and a “#4” (VBAC with a placenta abruption). I’ve always appreciated the doctors and nurses talking me through everything. It helps to know what’s going on, especially because time slows to a crawl and you wonder if everything’s OK down there!